Written by Dr. Matthew Capozzi, DPM, FACFAS, CWS (board-certified foot surgeon and wound specialist) · Medically reviewed by the CircuFiber Scientific Advisory Board · Updated: October 27, 2026
Diabetic ulcers are open sores that develop when high blood sugar damages the nerves and blood vessels, so minor pressure or injury breaks the skin and the wound struggles to heal. They most often form on the feet, especially the toes, heels and ball of the foot, but can also appear on the lower legs. The main causes are diabetic peripheral neuropathy, poor circulation and infection, and the biggest risks are deep infection, bone infection, gangrene and amputation. Early detection, pressure relief, professional wound care and good blood sugar control give an ulcer the best chance of healing.

Key Takeaways
- Diabetic ulcers are open wounds caused by diabetes-related nerve damage, poor circulation and repeated pressure, most often on the feet and sometimes on the lower legs.
- The three main causes are diabetic peripheral neuropathy (you cannot feel the injury), peripheral artery disease (not enough blood reaches the wound to heal it) and infection (which deepens the wound).
- Early signs include redness, swelling, drainage or blood on socks, a foul odor, thick cracked calluses and a sore that will not close, often without pain.
- Risk is highest with uncontrolled blood glucose, a long duration of diabetes and other complications such as kidney disease, heart disease or existing neuropathy.
- Treatment combines wound care and dressings, pressure relief, antibiotics for infection and, when needed, surgery to remove dead tissue or restore blood flow.
- See a doctor the same day for any open sore on a diabetic foot; untreated ulcers can lead to osteomyelitis, gangrene and amputation.
What are diabetic ulcers?
Diabetic ulcers are open sores or wounds that form when diabetes-related nerve damage and reduced blood flow allow small injuries to break through the skin and stop them from healing normally. The most common type is the diabetic foot ulcer, but similar wounds can develop on the ankle and lower leg. Diabetic ulcers, a common yet often overlooked complication of diabetes, can have a profound impact on a person's quality of life.
People with diabetes are more likely to develop diabetic foot ulcers than others, due to inadequate glycemic control and the presence of other risk factors such as peripheral neuropathy, calluses on their feet or deformities. If left untreated, they can lead to non-traumatic lower extremity amputations. It is essential that people living with diabetes take good care of their feet by wearing comfortable footwear and paying attention to any signs of a developing ulcer in order for them not to become serious complications.
Why do people with diabetes get ulcers?
People with diabetes get ulcers because high blood sugar damages the nerves that sense pain and pressure, narrows the arteries that deliver oxygen to the skin, and weakens the body's ability to fight infection. Any one of these problems makes a wound more likely; together they explain why a small blister or callus can turn into a deep, slow-healing ulcer.
Poor circulation and peripheral artery disease (PAD)
Diabetic foot ulcers, which are commonly caused by poor circulation, can have a variety of underlying causes. These include the buildup of plaque in arteries and veins, blood clots, narrowing of the vessels from obesity or diabetes-related issues such as heart conditions and high cholesterol levels. Peripheral artery disease (PAD) may also be present due to raised blood pressure or varicose veins. These symptoms should all be checked for using an Ankle Brachial Index test (ABI). People who suffer with flat feet could also develop more frequent instances of diabetic foot ulcers because extra stress on certain areas means inflammation can occur easily. Read more on improving foot circulation with diabetes.
Nerve damage (diabetic peripheral neuropathy)
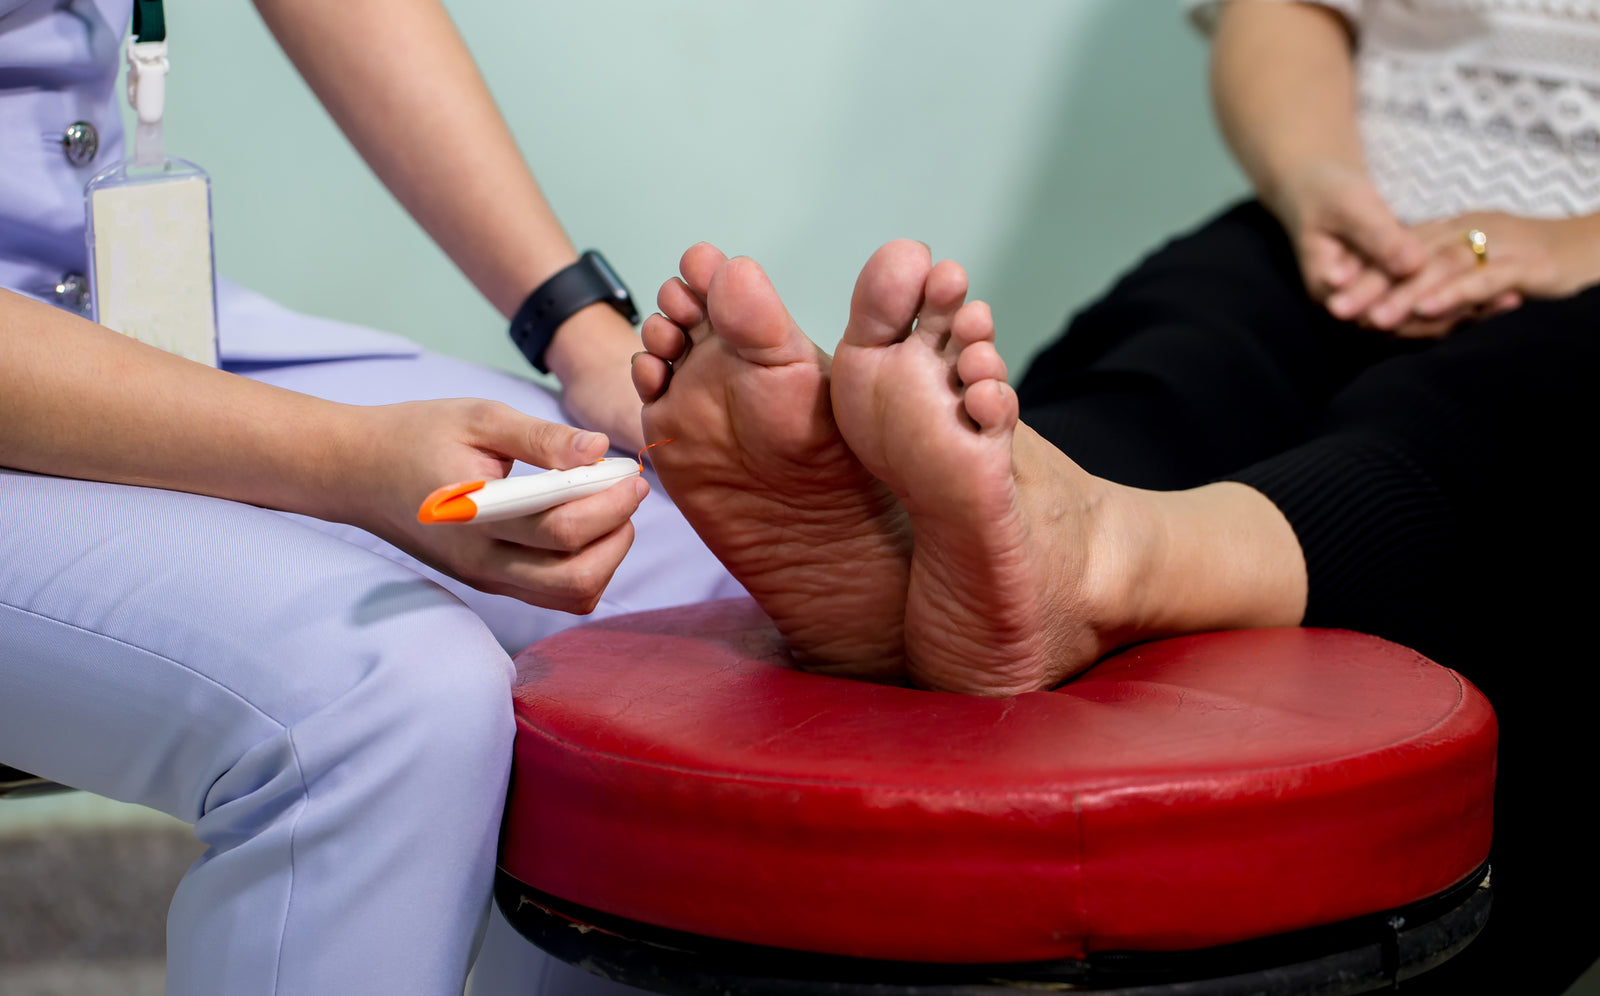
Around 60 percent of individuals living with diabetes suffer from peripheral neuropathy due to nerve damage, leading to a reduced sensation and an elevated risk for injury or ulceration. One form of foot ulcer that is especially common among those who have diabetic peripheral neuropathy is the neurotrophic ulcer, which typically emerges on pressure points such as the toes and the ball of the foot. Neurotrophic ulcers can be recognized by their raised, callused borders and a "punched-out" appearance.
Infection
Diabetic ulcers can be complicated by infections which may lead to additional tissue damage and impede the healing process. Cellulitis, myositis, abscesses, necrotizing fasciitis, septic arthritis and tendinitis as well as osteomyelitis have been linked to diabetic ulcers. If not addressed properly, these infections could potentially spread, causing severe health complications. To prevent this from occurring, treatments such as antibiotics for infection control should be taken up along with possible surgical interventions if needed. Our guide to diabetic foot infection management covers the warning signs in detail.
What are the symptoms of a diabetic ulcer?
The symptoms of a diabetic ulcer are an open sore, redness or discoloration, swelling, drainage or blood on your socks or shoes, a foul odor and thick, cracked calluses, often with little or no pain because of nerve damage. These types of wounds can be recognized by pain or discomfort, an unpleasant smell, noticeable redness or sores on the areas that bear weight such as heels, toes and around the metatarsal head. Diabetes-related blisters may also occur, along with swelling and drainage from socks or shoes containing blood. Thick calluses with splitting skin along with cracked feet are other telltale signs.
Visual appearance
A diabetic foot ulcer can be identified by certain alterations to the skin, such as modifications in color or odd-shaped edges. Diabetics with neuropathy should routinely examine their feet and toes when dressing. The length and depth of an ulcer may increase until it reaches bone level if not taken care of properly. Regular inspection is recommended in order to avoid complications that could arise from this condition. To see what the earliest changes look like, review our early-stage foot ulcer pictures.
Pain or discomfort
Many diabetic ulcers do not hurt, and the lack of pain can be attributed to decreased sensation in the feet due to neuropathy. Neuropathic pain, radicular discomfort and wound-related pain are typically linked with these types of sores when sensation is still present. When diagnosing or treating any form of diabetes-related blisters on the extremities, care needs to be taken regarding nerve damage that could lead to a loss of feeling around the areas affected.
Odor
The presence of a foul smell with diabetic ulcers is cause for alarm and should be addressed as soon as possible, since it may signal the onset of an infection that needs to be treated. Microorganisms such as bacteria are frequently the source behind this unpleasant odor. Immediate medical assistance is therefore essential.
The table below summarizes what each sign may mean and what to do about it.
| Sign | What it may indicate | What to do |
|---|---|---|
| Thick callus, cracked or splitting skin over a pressure point | Early pre-ulcer damage from repeated pressure | Book a diabetic foot exam; do not trim the callus yourself |
| Redness, warmth or swelling without an open sore | Inflammation or early infection | Call your podiatrist within 24 hours |
| Open sore, drainage or blood on socks | Established diabetic ulcer | See a doctor or podiatrist the same day |
| Foul odor, pus, spreading redness, fever | Infected ulcer (cellulitis or abscess) | Seek urgent care the same day |
| Black or dark tissue, a wound that reaches bone | Gangrene or osteomyelitis | Seek emergency care |
Who is most at risk for diabetic ulcers?
The people most at risk for diabetic ulcers are those with poorly controlled blood glucose, a long history of diabetes and other diabetes complications such as neuropathy, kidney disease or heart disease. Knowing these risks is fundamental in order to both reduce the chances of getting a diabetic foot ulcer and successfully manage them should they occur. Early discovery and treatment are vitally important to minimize potential infection or amputation.
Uncontrolled blood glucose levels
Diabetic patients with uncontrolled blood glucose levels can be more vulnerable to developing ulcers. High sugar concentrations in the bloodstream may inflict nerve damage and impede proper circulation, impeding wound healing, which boosts the chances of forming sores, particularly around the feet. Peripheral neuropathy caused by diabetes is marked by inflammation and thickening of nerves, resulting in sensations such as tingling or numbness, along with narrowed arteries that struggle to provide oxygen-rich blood to the lower limbs.
Diabetes duration
Having diabetes for an extended period of time contributes to a greater chance of developing diabetic ulcers, because nerve and blood vessel damage accumulate over the years. Early diagnosis and treatment are key in order to help reduce potential complications that might otherwise arise from longer durations living with diabetes.
Presence of other diabetes-related complications
Individuals with diabetes are more likely to develop diabetic ulcers due to having other health complications. These can include heart disease, chronic kidney disease and damage or dysfunction in the nerves, feet, mouth, eyesight, hearing ability and skin, as well as digestive problems or sexual difficulties. Foot issues such as decreased blood flow that impairs wound healing capability, along with nerve damage, increase the probability of acquiring an ulcer even further.
How are diabetic ulcers treated?
Diabetic ulcers are treated by relieving pressure on the wound, cleaning and dressing it, controlling infection with antibiotics and, when necessary, surgery to remove dead tissue or restore blood flow. The choice of treatment for such wounds depends on the severity, location and presence or absence of infection or lack of blood flow (ischemia). Early diagnosis and intervention will help avoid serious issues resulting from these types of lesions.
How doctors classify a diabetic ulcer
Diabetic ulcer classification systems, such as the Wagner or University of Texas models, consider the depth of the wound along with infection and ischemia in determining how to treat a patient. An assessment of the depth is necessary to ascertain how serious a diabetic ulcer is: visual inspection, probing or imaging tests such as ultrasound or MRI can all be used to evaluate tissue damage and identify any infection present. To identify infection and poor blood flow, doctors may order blood tests, imaging exams or a physical assessment. Using these systems, healthcare practitioners can decide on an optimal treatment plan, which may be anything from wound care and dressings to antibiotics to surgical procedures. Our guide to the stages of diabetic foot ulcers explains each grade.
Wound care and dressings
The purpose of wound care and dressings is to protect the ulcer, stimulate healing, manage exudate flow and reduce infection risk. It is important that mild soap and water be used for cleaning, followed by thorough drying before applying any type of dressing. Dressing options range from hydrocolloids to alginates; foams or hydrogels can also be considered depending on the condition of the area. The frequency at which a particular dressing needs changing may vary between 1 and 7 days, depending on the kind of dressing and how much progress the ulcer has made. Your wound-care team will also relieve pressure on the ulcer with special footwear, an offloading boot or a cast.
Antibiotics for infections
For treating bacterial infections in diabetic ulcers, antibiotics may be prescribed depending on the type and severity of infection. Antibiotics that may be used for this purpose include cephalexin, dicloxacillin, amoxicillin-clavulanate, clindamycin, vancomycin and piperacillin/tazobactam. It is essential to keep a check on how the infection responds to these treatments, and changes may be needed based on what works best against it.
Surgical interventions
In order to promote healing of serious and non-healing ulcers, surgical interventions may be needed. These can range from debridement (the removal of unhealthy tissue) to bone resection, revascularization for restoring blood flow in the affected region and, in the most severe cases, amputation. Vascular surgeons work together with the rest of the care team when deciding on which procedure would best suit an individual patient's needs.
Which specialists treat diabetic ulcers
The management of diabetic ulcers necessitates an interprofessional approach involving podiatrists, endocrinologists and vascular surgeons. Podiatrists perform assessments for foot deformities, diagnose and treat diabetic ulcers, provide wound treatment and dressings, and give ongoing education about prevention. Endocrinologists oversee and manage blood glucose levels, provide guidance on dietary habits and lifestyle changes, and prescribe medications if necessary. Vascular surgeons provide medical and surgical care for vascular conditions, through medications, endovascular interventions or open surgery, and handle severe cases requiring revascularization. Not sure where to start? Read our guide to choosing a diabetic foot specialist.
What complications can diabetic ulcers cause?
Diabetic ulcers can cause deep infection, bone infection (osteomyelitis), tissue death (gangrene) and amputation if they are left unchecked. Early intervention is paramount to avert these complications, which can also damage mental health, mobility and social life.
Osteomyelitis
An infection of the bone, called osteomyelitis, can occur when diabetic ulcers are not treated or managed properly. Diagnostic methods for identifying this condition include a probe-to-bone test and imaging tests such as MRI scans. It is essential to detect it early in order to avoid lasting damage, with prompt medical attention and treatment programs customized to individual needs.
Gangrene
In extreme cases of diabetic ulcers, tissue death (gangrene) may occur and surgery could be necessary to treat it. Antibiotics may help clear the infection, along with surgical removal of the dead areas and skin grafts to replace damaged skin. In more serious situations, amputation might have to be an option. See our article on diabetic foot gangrene treatment.
Amputation
In some cases, amputation may be required when ulcers are severe or do not heal, greatly affecting one's quality of life. This is often the case with major lower extremity amputations (MLEA), including those done below the knee due to diabetic ulcer conditions. Following an operation like this, physical therapy and occupational therapy sessions will need to take place, along with being fitted for a prosthesis.
Impact on quality of life
Diabetic ulcers can have a substantial impact on an individual's well-being, interfering with their mental health, physical capability and social life. When present chronically, they can have an adverse effect on mental health such as depression and anxiety, so treatment should include the psychological aspects and appropriate support. Diabetic ulcers can lead to painful sensations and amputations, negatively impacting mobility and daily activities. The appearance and odor of a wound that requires ongoing medical care can also cause social stigma and feelings of shame, which may lead to isolation and decreased quality of life. It is vital to focus not just on treating the wound but on all aspects of care that surround the person.
How can you prevent diabetic ulcers?
You can prevent most diabetic ulcers by inspecting your feet daily, keeping blood glucose in your target range, wearing properly fitting shoes and socks, never going barefoot and seeing a podiatrist regularly. With the right preventive strategies in place, complications arising from these kinds of wounds may be avoided or at least minimized significantly.
Proper foot care
Adhering to the right kind of foot care is important for reducing one's risk of diabetic foot ulcers. This includes inspecting feet daily, keeping them clean and dry, wearing shoes that fit properly, and never going barefoot when walking. As part of a regular routine, wash any small cuts or blisters with soap and water before drying carefully. Applying moisturizing lotion (but not between the toes) can help preserve hydration levels. Never cut corns or calluses yourself, and ask your podiatrist before using a pumice stone or file on thickened skin; antifungal creams can help prevent fungal infections which may develop. Ultimately your choice in footwear should be comfortable yet well fitting, as this plays an integral role in guarding against injuries that can lead to ulceration.
Blood glucose management
For the prevention of diabetic foot ulcers, good management of blood glucose is vital. This includes keeping up a healthy diet, engaging in regular physical activity and adhering to any prescribed medication regimen. By ensuring optimal levels of sugar in the bloodstream, it can help lessen nerve damage as well as poor circulation, which are both possible causes of foot ulcers related to diabetes.
Regular check-ups with healthcare professionals
It is of utmost importance that people at risk of diabetic foot ulcers make regular visits to healthcare professionals. This includes scheduling appointments with a doctor or podiatrist on a frequent basis for inspections and performing blood tests routinely to keep track of one's glucose levels. Consultations can help detect any evidence of impending ulcers at an early stage as well as provide advice on prevention.
Can diabetic socks help with diabetic ulcers?
Diabetic socks can help protect intact skin from the friction, pressure and moisture that lead to ulcers, but they are not a treatment for an existing wound; an open ulcer needs professional wound care and whatever dressing or offloading device your care team prescribes. For prevention, a good diabetic sock is seamless so there is no ridge rubbing over the toes, has a non-binding top that does not squeeze the calf or restrict blood flow, is moisture-wicking to keep skin dry, and is padded to cushion pressure points. For a detailed comparison, see our guide to diabetic socks vs. compression socks.
CircuFiber diabetic socks are designed with all of those features and go a step further. The fabric is woven with Circulight® IR fibers containing thermoreactive mineral particles that absorb your own body heat and reflect it back into the foot as far-infrared energy, which promotes a temporary increase in local blood flow and circulation. In a randomized, double-blinded, placebo-controlled trial at Yale School of Medicine (ClinicalTrials.gov NCT04460612, published in Diabetes & Vascular Disease Research, 2023), the active textile significantly increased transcutaneous oxygen in the feet of people with diabetes compared with a placebo sock, with the difference visible at 40 minutes and significant at 60 minutes. CircuFiber socks also carry the APMA Seal of Acceptance.
What this means in practice: wear them daily over healthy, intact skin as part of your prevention routine, and if you already have an ulcer, ask your podiatrist what to wear over the dressing.
When should you see a doctor about a diabetic ulcer?
See a doctor or podiatrist the same day you notice any open sore, blister, drainage, blood on your socks or a foul odor on a diabetic foot, even if it does not hurt. Go to urgent or emergency care if there is spreading redness, pus, fever, black or dark tissue, or a wound deep enough to see tendon or bone. Leaving a diabetic ulcer untreated, even for a few days, allows infection to spread to deeper tissue and bone. People with diabetes should also have a comprehensive foot exam at least once a year, and more often if neuropathy, circulation problems or a previous ulcer have already been diagnosed.
Frequently asked questions about diabetic ulcers
What does a diabetic ulcer look like?
A diabetic ulcer usually looks like a round, open sore with redness at its borders and thickened, callused skin around it, most often on the ball of the foot, the toes or the heel. The wound may drain clear fluid, pus or blood. Diabetic ulcers can become very serious, exposing bones and tendons if they are not treated.
What are the first signs of a diabetic ulcer?
The first signs of a diabetic ulcer are discoloration of the skin, swelling, warmth, a thick callus with cracking, drainage on your socks and, eventually, an open sore. Tingling or numbness in the feet is a warning that nerve damage is present and an ulcer could form without you feeling it. Early detection is key to receiving efficient treatment before it develops into more serious complications.
Can diabetic ulcers go away?
Yes, most diabetic ulcers can heal with proper diagnosis and treatment. Regular monitoring of the affected area, reducing pressure on the wound site and specific therapies such as dressings, debridement or antibiotics may need to be employed for a successful recovery. The time required varies, but it typically takes up to three months until full healing is achieved, and ulcers can recur without ongoing foot care.
Can you get a diabetic ulcer on your leg?
Yes. Diabetic ulcers on the lower leg are usually linked to poor circulation, either peripheral artery disease (arterial ulcers, often on the shin or ankle) or vein problems (venous ulcers, usually just above the ankle), and they are evaluated and treated differently from pressure-related foot ulcers. Any non-healing sore on the leg of a person with diabetes should be examined by a doctor.
Can you die from a diabetic foot ulcer?
A diabetic foot ulcer itself is rarely fatal, but a severely infected ulcer can lead to sepsis, gangrene and amputation, which carry serious health risks. This is why same-day medical attention for an infected ulcer, and prevention in the first place, matter so much.
Can people without diabetes get foot ulcers?
Yes. Foot ulcers in people without diabetes are usually caused by poor circulation, vein disease, prolonged pressure or nerve damage from other causes. Our article on non-diabetic foot ulcers explains how they differ.
References, studies and sources
- Ariani, Y., Tarigan, R. B., Pase, A. (2017). Foot Care and Risk of Diabetic Foot in Patients with Type 2 Diabetes at H. Adam Malik Hospital Medan. Proceedings of the 1st Public Health International Conference (PHICo 2016). https://doi.org/10.2991/phico-16.2017.38
- Pakaya, N., Kusnanto, K., Notobroto, H. B., Triyoga, R. S. (2021). Personal Agency Enhancing Model in Prevention of Diabetic Foot Ulcer. Jurnal Aisyah: Jurnal Ilmu Kesehatan, (6). https://doi.org/10.30604/jika.v6is1.762
- American Diabetes Association. Foot Complications. https://diabetes.org/about-diabetes/complications/foot-complications
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Diabetes and Foot Problems. https://www.niddk.nih.gov/health-information/diabetes/overview/preventing-problems/foot-problems
- American Podiatric Medical Association. Diabetic Wound Care. https://www.apma.org/patients-and-the-public/conditions-affecting-the-foot-and-ankle/diabetic-wound-care/
About the author: Dr. Matthew Capozzi, DPM, FACFAS, CWS, is a board-certified foot surgeon through the American Board of Foot and Ankle Surgery. He is a Diplomate of the American Academy of Wound Management and Fellow of the American College of Foot and Ankle Surgeons. He completed a three-year residency program in Foot and Ankle Reconstructive Surgery at St. Francis Hospital & Medical Center in Hartford, CT in 2010. Dr. Capozzi is a board-certified Wound Specialist® granted by the American Academy of Wound Management.
Healthcare disclaimer: Always consult your physician before beginning any program. This general information is not intended to diagnose any medical condition or to replace your healthcare professional. If you experience any pain or difficulty, stop and consult your healthcare provider. CircuFiber socks are a general wellness product intended to promote a temporary increase in local blood flow and circulation; they are not intended to diagnose, treat, cure, or prevent any disease. Individual results vary.